Summary:
You’ve rested. You’ve done the physical therapy. You’ve taken the anti-inflammatories. And you’re still waking up every morning with the same pain you’ve been carrying for months — maybe years. At some point, the question stops being “what’s wrong with my back?” and starts being “what actually comes next?”
For a lot of people living with chronic back pain across New York City, an epidural steroid injection is that next step. Not a last resort. Not a leap toward surgery. A targeted, evidence-based option that can change what’s possible. This post is here to help you figure out whether it makes sense for you.
What Is an Epidural Steroid Injection and How Does It Work?
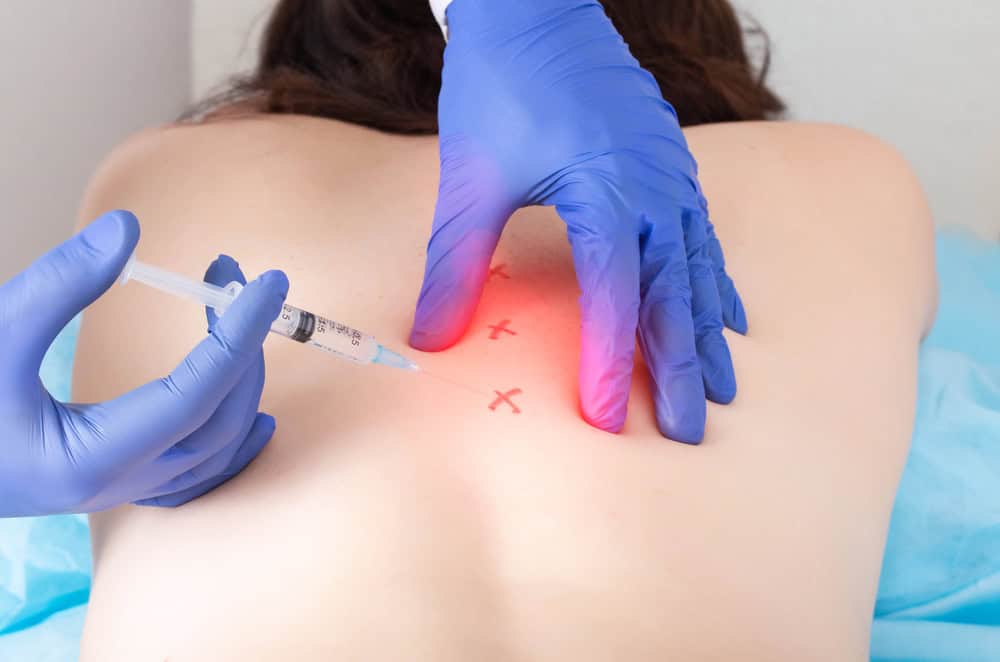
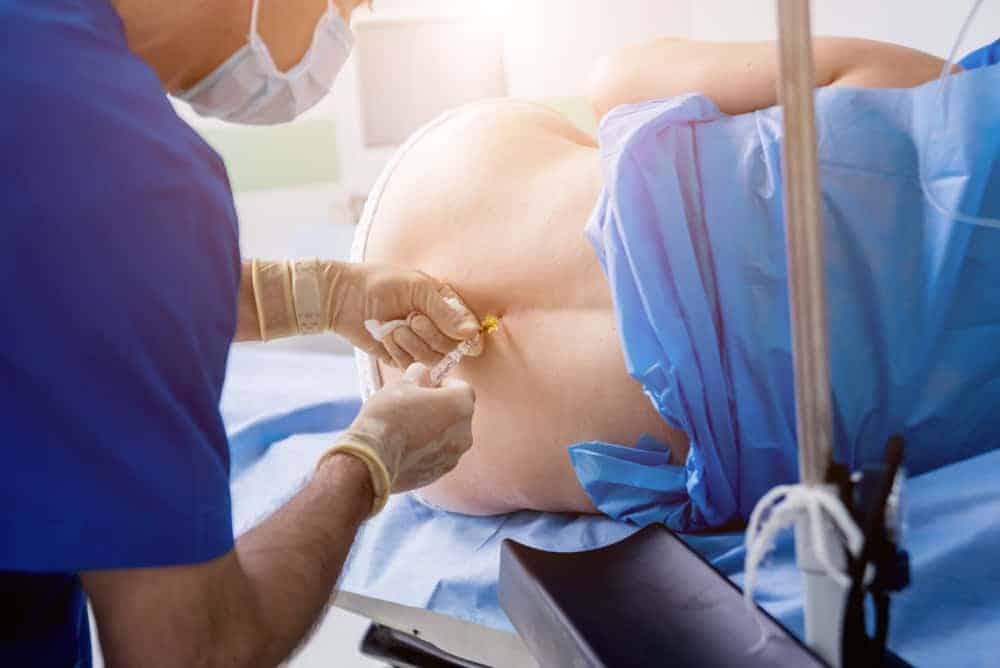
An epidural steroid injection — or ESI — delivers a corticosteroid medication directly into the epidural space of your spine, right around the nerve roots that are being compressed or irritated. The goal is to reduce inflammation at the source, which is what’s causing the pain, the burning, the numbness, or the weakness that radiates down your leg or arm.
This is not the same as a labor epidural. That procedure uses anesthetic to block sensation across a wide area. An ESI is far more targeted — it’s aimed at a specific spinal level identified through imaging, and it’s designed to calm the inflammation around a particular nerve. When it works, it doesn’t just dull the pain. It creates a window where your body can actually start to recover.
Which Conditions Does an Epidural Injection Actually Treat?
ESIs are most commonly used for conditions where a nerve is being compressed or irritated by something structural — a herniated disc pressing against a nerve root, spinal stenosis narrowing the canal, degenerative disc disease that’s created ongoing inflammation, or sciatica that sends shooting pain down one or both legs. If your pain has a clear nerve-related component — meaning it radiates, burns, tingles, or causes weakness in your limbs — you’re likely in the category of patients this treatment was designed for.
That said, not everyone with back pain is a candidate. If your pain is purely muscular, or if the underlying structural problem is severe enough that conservative treatment won’t address it, an ESI may not be the right tool. That’s exactly why the first step isn’t the injection — it’s the evaluation. A thorough review of your imaging, your history, and your symptoms is what determines whether this approach makes clinical sense for you specifically.
The conditions that respond best to ESI tend to share a common thread: inflammation is playing a central role in the pain. Disc herniations, for example, don’t just cause pain by physically pressing on a nerve — they also trigger a local inflammatory response that can be just as responsible for the radiating pain as the mechanical compression itself. Corticosteroids are among the most effective anti-inflammatory agents available, and delivering them directly to the affected area — rather than taking an oral medication that has to travel through your entire system — is what makes this approach meaningfully different from the medications most people have already tried.
Research published in Cureus found that transforaminal ESIs achieved greater than 50% pain improvement in over 64% of patients for pain at rest and more than 74% for nighttime pain at three months. A separate 2025 retrospective study found that pain relief from ESI can last up to a full year in some patients. Those aren’t guarantee numbers — but they’re meaningful, and they’re based on real clinical data, not promotional claims.
Does an Epidural Injection Help You Avoid Surgery?
This is one of the most important things to understand about ESI, and it’s something that often gets lost in the standard explanation. An epidural injection is not a cure. It doesn’t fix a herniated disc or reverse spinal stenosis. What it does is reduce the inflammation and pain enough that your body — and your physical therapy — can do the work that actually leads to long-term improvement.
Think of it this way: if the pain is so severe that you can’t move well, can’t participate in rehabilitation, and can’t sleep, your body has no real opportunity to heal. The injection creates the breathing room. Physical therapy, done in that window of reduced pain, can strengthen the muscles that support your spine, correct the movement patterns that contributed to the problem, and help you build a more sustainable baseline. That’s the combination that helps people avoid surgery — not the injection alone, but the injection as a bridge to active recovery.
The American Academy of Neurology found that compared to patients who received no ESI treatment, 24% more ESI patients reported reduced pain and 16% more reported reduced disability at three months. For patients with spinal stenosis specifically, 26% more reported reduced disability at three months, and 12% more at six months or beyond. These numbers matter because they reflect what happens in real patient populations — not controlled lab conditions.
It’s also worth being honest about the limits. If the first injection provides no relief at all, subsequent injections are less likely to help, and a good provider will tell you that upfront. We recommend no more than three injections within a twelve-month period. The goal is never to keep injecting indefinitely — it’s to use the treatment strategically as part of a broader plan that includes rehabilitation and, when appropriate, lifestyle changes.
Want live answers?
Connect with a NY Spine Medicine expert for fast, friendly support.
What NYC Patients Should Know Before Getting a Spinal Injection
New York City puts a specific kind of wear on the spine. The daily grind of a packed subway commute — standing on a crowded 4/5/6 train with a bag on one shoulder, holding a pole at an awkward angle for forty-five minutes — is a real and recurring source of spinal stress. Add long hours at a desk in Midtown, walking miles on hard pavement, or the physical demands of construction, healthcare, or delivery work across Brooklyn, Queens, the Bronx, and Staten Island, and you’ve got a city that generates chronic back pain at scale.
That context matters when you’re choosing a provider. We understand what your body has been through and what a realistic recovery looks like given the demands of your life in New York City.
How to Know If You're Seeing the Right Pain Management Doctor in NYC
The quality of an epidural steroid injection is not uniform across providers. Two of the most important things to look for are board certification in interventional pain management and the use of fluoroscopic — meaning image-guided — injection technique. Fluoroscopy is real-time X-ray guidance that allows the physician to confirm exactly where the needle is placed before delivering the medication. It’s the current standard of care, and it meaningfully improves both accuracy and safety. Not every provider uses it for every injection, and that gap matters.
Beyond the technical side, the diagnostic process matters just as much. A provider who recommends an injection on your first visit, before reviewing your imaging or understanding your full history, is skipping the step that determines whether the injection is even appropriate for your specific condition. The right approach starts with a thorough evaluation — your MRI, your symptoms, how long you’ve been dealing with this, what you’ve already tried — and works forward from there.
In a city with as many pain management options as New York City, the credential that stands out most is dual board certification in both interventional pain management and neurology. It’s exceptionally rare — fewer than 200 physicians in the country hold it — and it’s directly relevant for back pain patients whose symptoms include nerve-related components like sciatica, radiculopathy, or neuropathy. A physician trained in both disciplines understands not just the structural source of the pain, but the neurological pathway it travels through. That distinction changes the diagnostic picture and, often, the treatment plan.
Dr. Douglas Schottenstein holds exactly that dual certification. He has been practicing for over 25 years and is credentialed at Lenox Hill Hospital and several other major medical centers across the region. Patients consistently describe his approach as thorough, unhurried, and clear — he takes the time to walk through imaging results and explain what’s actually happening and why. That kind of communication isn’t a bonus feature. For a procedure involving your spine, it’s the baseline you should expect.
Common Questions About Epidural Injections — Answered Honestly
The most common question patients ask is some version of: “Will this actually work for me?” The honest answer is that ESI works well for a significant portion of the right candidates — but it doesn’t work for everyone, and the outcome depends heavily on the underlying condition, the precision of the procedure, and what happens in the weeks after the injection. It’s the accurate answer, and any provider who promises guaranteed results is overselling.
A close second is: “Is it going to hurt?” The procedure itself involves a needle placed near the spine, which sounds alarming. In practice, the area is numbed with a local anesthetic first, and most patients describe the sensation as pressure rather than sharp pain. The procedure typically takes less than thirty minutes, and most people go home the same day. Some patients feel relief within a few days; for others it takes one to two weeks for the corticosteroid to reach its full effect.
People also ask whether they’ll become dependent on injections, or whether the steroids will cause long-term harm. At the doses used in ESI and with the frequency limits in place — no more than three per year — systemic side effects are uncommon. This is very different from long-term oral steroid use. The goal is never ongoing injection dependency; it’s a targeted intervention that creates the conditions for lasting improvement through rehabilitation.
For patients across Manhattan, Brooklyn, Queens, the Bronx, and Staten Island, one practical question is simply access. Our office at 18 East 48th Street in Midtown Manhattan is steps from Grand Central Terminal, which means it’s reachable by subway from every borough and by commuter rail from across the tri-state area. You don’t need a car, and you don’t need to take a full day off work. That matters in a city where getting to a specialist appointment is its own logistical challenge. We serve patients from neighborhoods across every borough — from East New York to Long Island City to Staten Island — because chronic back pain doesn’t confine itself to one zip code.
Is an Epidural Injection the Right Next Step? Here's How to Find Out
If you’ve been living with chronic back pain that hasn’t responded to the basics — rest, physical therapy, medication — an epidural steroid injection may genuinely be the next right move. Not because it’s a last resort, but because it’s a targeted, evidence-backed treatment that, for the right patient, can change what’s possible. The key is making sure you’re actually the right patient, which requires a real evaluation from a physician who takes the time to understand your specific situation.
The question isn’t just whether ESI works in general. It’s whether it’s the right tool for your condition, your imaging, and your goals — and whether you’re working with someone who has the training to answer that honestly.
If you’re ready to get a clear answer, we at NY Spine Medicine are here to help. Reach out to schedule a consultation and find out whether an epidural injection belongs in your treatment plan — or whether something else makes more sense first.