Summary:
Plenty of tests get ordered because they are available. The better question for any test is what you would do differently depending on the result, and for electromyography in muscle and nerve disorders that answer is unusually concrete.
A report describing a muscle based pattern sends the evaluation in one direction. A report that localizes damage to a single nerve root sends it in another. A report showing old changes without any active ones may argue against doing anything invasive at all.
This is about that step, the one between the result and the plan, which is rarely explained to the person the plan actually belongs to.
Treating The Right Problem Starts With Naming It Correctly
Most treatment failures in this area are not failures of technique. They are failures of targeting.
A course of therapy aimed at the shoulder will not help weakness caused by a cervical nerve root. Wrist surgery will not help numbness that originates in the neck. An anti inflammatory program will not do much for weakness caused by a medication nobody has reviewed. Each of those treatments is perfectly reasonable applied to the right problem, and useless applied to the wrong one.
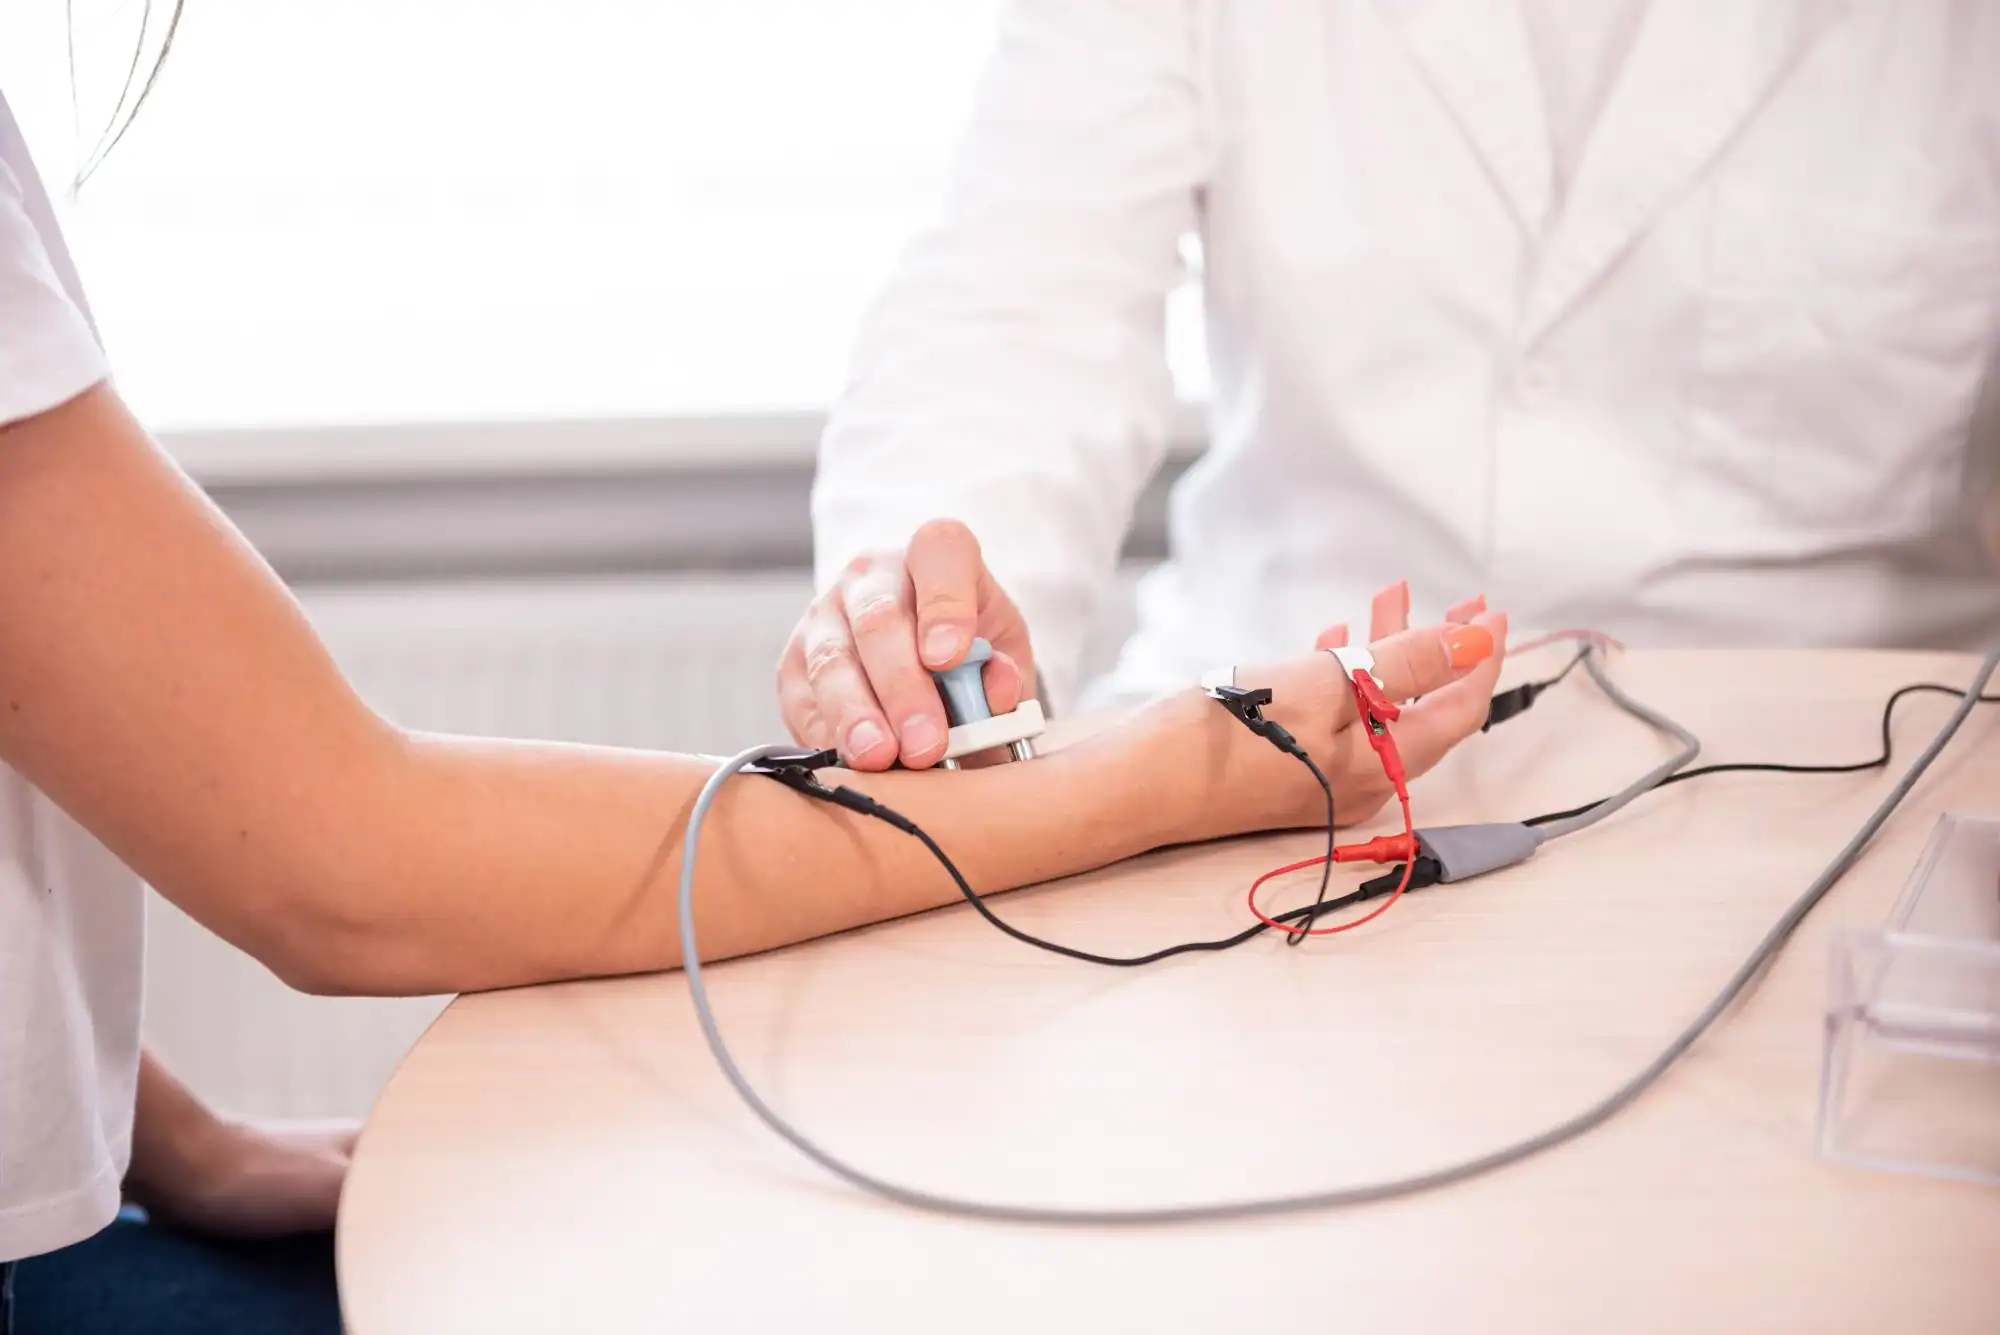
Electromyography and nerve conduction testing establishes the category before resources are committed. It says whether the trouble is in muscle, in nerve, or at the junction between them, and if it is in nerve, where along the path. Everything downstream, the referrals, the imaging, the injections, the exercise plan, follows from that.

How Do EMG Findings Change The Treatment Plan?
A report contains more than a yes or a no, and each element points somewhere specific.
Location changes what gets treated. A finding at the nerve root directs attention to the spine, which may mean an epidural or a selective nerve root injection at that level. A finding at a peripheral nerve directs attention to that site instead, which may mean splinting, an image guided injection, activity modification, or a surgical referral. A muscle based pattern moves the case away from the spine entirely.
Severity changes urgency. Mild slowing without loss of fibers supports continuing conservative care, because there is time and the potential for full recovery. Evidence of significant fiber loss, particularly alongside weakness, shortens the timeline for deciding whether to relieve the pressure more definitively.
How long the process has been going on changes expectations. Findings suggesting an old, stable problem predict slower recovery and argue for a plan built around function rather than around reversing damage. Findings suggesting a recent, active process are more likely to respond to prompt treatment.
Distribution changes the workup. Many nerves involved symmetrically points toward a systemic cause, which means the treatment is often metabolic, nutritional, or a medication change rather than anything procedural.
And a normal study changes the plan too. It removes an assumption, and it usually redirects the search toward a joint, a tendon, circulation, or a source of referred pain that would otherwise have been overlooked.
When Results Support Surgery, And When They Argue Against It
This is where objective testing carries the most weight, because the stakes of guessing are highest.
Results tend to support surgical consideration when the findings match the symptoms and the imaging, when they localize to a level or a site that can be addressed, and when there is evidence of ongoing nerve compromise rather than an old stable change. Progressive weakness with clear loss of nerve supply in the muscles served by one root is a very different conversation from pain alone.
Results argue against surgery when they are normal despite impressive imaging, when the abnormality does not correspond to the level that was going to be operated on, or when the findings show a generalized process rather than a focal one. Operating on a disc in someone whose real problem is a diabetic neuropathy will not help the burning in their feet, and that is an avoidable mistake.
There is also a middle situation worth naming. Chronic changes without active ones sometimes mean the damage is old and the current pain is coming from something else. Surgery in that setting may address a finding without addressing the complaint.
None of this replaces surgical judgment or the rest of the picture. It informs it. A responsible surgical decision rests on symptoms, examination, imaging, and function, with electrical testing as the piece that confirms whether the anatomy on the scan is actually doing anything.
Want live answers?
Connect with a NY Spine Medicine expert for fast, friendly support.
Using Findings To Aim Injections And Target Therapy
Interventional treatment is only as good as its target, and this is where a report becomes practical.
If testing localizes the problem to a specific nerve root, an injection can be directed at that level rather than at the level that simply looks worst on imaging. Those two are not always the same, and the difference between them is often the difference between a helpful injection and a wasted one.
Therapy gets sharper too. Knowing which muscles are affected, and how severely, lets a physical therapist load the right tissue and protect what should not be loaded yet. A muscle that has lost nerve supply needs a different approach from one that is simply deconditioned, and a muscle based process needs a different approach again.
It also sets a baseline for later comparison, which is far more reliable than trying to compare against memory six months from now.
What Severity And Chronicity On The Report Mean For Recovery
These two words appear in most reports and are almost never explained to the patient holding the page.
Severity describes how much of the nerve or muscle is affected. At the mild end, conduction is slowed but the fibers are intact, and the outlook is generally good once whatever is causing it has been addressed. At the more severe end, fibers have been lost, and while treatment can stop further loss and improve symptoms, rebuilding takes time. Nerve fibers regrow slowly, and function does not always return completely.
Chronicity describes how long the process appears to have been going on. Acute changes suggest something recent. Chronic changes suggest a process your body has already partly compensated for. Reports often describe both together, because an old problem can flare, and a chronic pattern carrying new active changes is a meaningful finding in itself.
What this means for you is mostly about timeline and expectation. A mild, acute finding often justifies a few months of conservative treatment with a good chance of resolution. A severe, chronic finding calls for a plan focused on preserving what works, adapting how tasks are done, and managing symptoms, alongside honest conversations about how much is likely to come back.
Neither result is a verdict. People with significant findings often do very well functionally, and people with mild findings sometimes struggle, because symptoms and electrical measurements are related but not identical. The report describes the wiring. It does not describe your life.
What it does do is end the cycle of trying one thing after another with no way to tell whether any of it is working.
Why Objective Testing Matters In Work Injury And Auto Injury Cases
If your injury happened at work or in a car accident, there is a second audience for your results, and it is not a sympathetic one.
Insurers and adjusters weigh documented findings differently from reported symptoms. Pain is real, but nobody other than you can measure it. Nerve conduction values and needle findings are measurements, recorded by equipment, interpreted by a physician, and reproducible. That is why they carry weight in a claim that pain descriptions alone do not.
Testing also speaks to timing, at least in general terms. An experienced electromyographer can often say whether a pattern looks recent or long standing, which matters when a claim turns on whether an injury caused the problem or revealed something that was already there. The test cannot date an injury precisely, and any report claiming to do that deserves skepticism, but the broad distinction between recent and chronic is genuinely informative.
It matters for treatment authorization as well. Procedures and surgery are frequently approved or denied on the basis of documented objective findings. A well performed study that supports the clinical picture removes one of the common reasons for delay, and delay in these cases is not neutral, because prolonged nerve compression has a cost.
Two practical points. First, have the testing done where the results will be interpreted alongside your care rather than in isolation, because a report that arrives with no context tends to generate more questions than it answers. Second, keep your own copy of the report and the underlying data, not only the summary letter, since a claim tends to outlast the memory of everyone involved in it.
And regardless of any claim, some symptoms need attention before any paperwork. Weakness that is getting worse, numbness in the groin or inner thighs, loss of bowel or bladder control, or severe pain following significant trauma all require prompt evaluation.
From Test Result To A Treatment Plan That Makes Sense
The real takeaway is that the point of electromyography is not the report. It is the set of decisions the report lets you make with confidence, including the decision not to do something.
A better frame: a test that does not change the plan was not worth having, and a test that does change the plan is worth doing early rather than after several rounds of trying things and hoping. In muscle and nerve disorders, that fork usually shows up near the beginning, not at the end.
At NY Spine Medicine, our Manhattan and Brooklyn offices perform the testing, interpret it, and deliver the treatment that follows from it, including injections, physical therapy, and coordination with surgery when it is warranted. We also handle workers compensation and auto injury cases regularly, so the documentation is prepared with those requirements in mind from the start.
If you have a study coming up, a report nobody has explained to you, or symptoms that still have not been sorted out, call us at 212-750-1155.