Summary:
Almost every new patient arrives with a theory. Some are convinced they will be handed opioids and sent away. Others are convinced they will be told to live with it. A few have been told by a relative that injections destroy your bones.
None of these ideas come from nowhere. They come from a friend who had a bad experience, an article from fifteen years ago, or a rushed appointment where nobody explained anything.
They matter because beliefs drive behavior. Patients who think pain management means pills avoid it. Patients who think it is a last resort wait years. Here are eight worth correcting.
Myth One: Pain Management Just Means Prescribing Pills
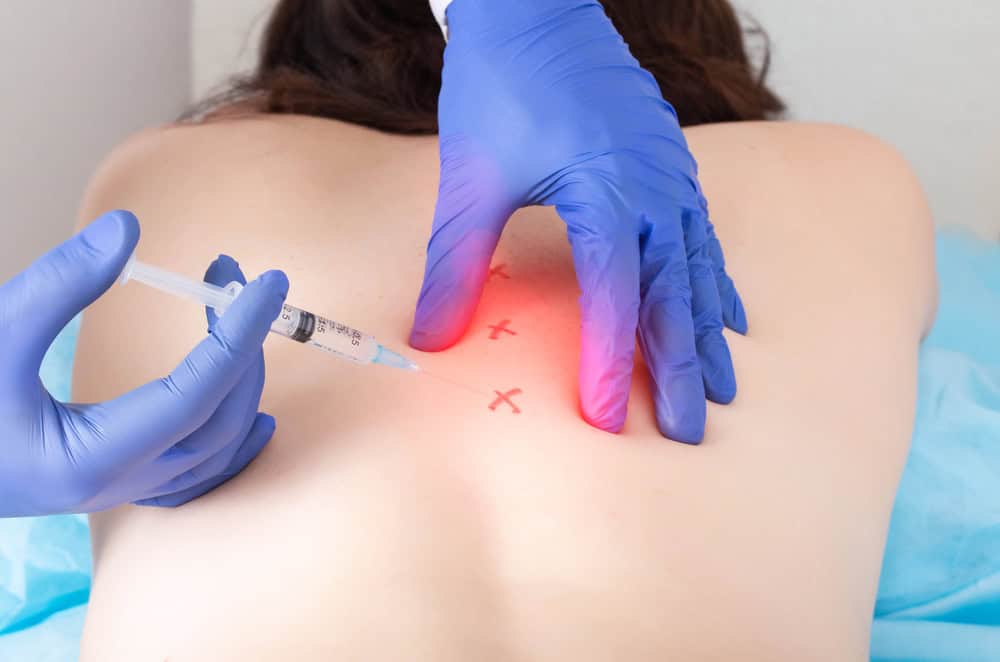
This is the most persistent one, and it is close to the opposite of how the specialty works today. Interventional pain management is procedural. The core of it is identifying which structure is producing your pain, then treating that structure directly with image guided injections, nerve blocks, radiofrequency ablation, or neuromodulation, alongside physical rehabilitation.
Medication has a role, but a narrower one than patients expect. It is generally used to make you functional enough to participate in the rest of the plan, not as the plan itself. Many patients treated in a pain practice take less medication over time rather than more, precisely because the source of the pain is being addressed. If a physician offers you a prescription and no diagnostic reasoning, that is a reason to ask more questions, not a description of the field.

Myths Two And Three: Is It A Last Resort, And Is It Real?
The second myth is that pain management is what you do after surgery has failed. In practice, most patients who come through a pain practice never have spine surgery at all, and many are referred long before surgery is ever discussed. Pain management sits in the middle of the spectrum, between conservative care and the operating room, and it is often the step that makes surgery unnecessary.
Waiting has a cost. Pain that has been present for years is harder to treat than pain that has been present for months, partly because the nervous system becomes more efficient at producing it and partly because months of guarding and inactivity leave you weaker. None of this means every ache needs a specialist, but pain that has not improved after six weeks of reasonable care deserves a look. Earlier evaluation is not being dramatic. It is usually the cheaper path in every sense.
The third myth is that if the MRI looks unremarkable, the pain must not be real, or must be in your head. This one causes genuine damage, because patients start to doubt themselves. Imaging shows structure. It does not show pain. Several truly painful conditions are largely invisible on a standard MRI, including facet mediated pain, sacroiliac joint dysfunction, small fiber neuropathy, and myofascial pain.
The reverse is just as true. Plenty of people walk around with impressive looking disc bulges and no symptoms whatsoever. That is why a careful history and physical exam outrank the radiology report, and why diagnostic blocks exist. When a numbing injection to a specific structure reliably takes your pain away, that is direct evidence about the source, and no scan is required to validate it. Nobody serious in this field thinks unexplained pain is imaginary.
Myths Four And Five: Band Aids, And Waiting Until It Is Bad Enough
The fourth myth is that injections are just a band aid that fixes nothing. There is a grain of truth buried in it, which is why it survives. An epidural steroid injection does not repair a disc, and a facet block does not reverse arthritis. But treating pain as though it were purely a signal to be endured misses what pain actually does to a body.
Pain stops you from moving. Not moving makes you weaker, stiffer, and more sensitized, which produces more pain. An injection that interrupts that loop for six or eight weeks is not cosmetic. It is what allows physical therapy to be effective, and in many conditions, including disc herniations, it buys time while the underlying problem resolves on its own. Injections also serve a diagnostic purpose that nothing else replicates, since the response tells your physician which structure is actually involved.
The fifth myth is that you have to be in severe pain, or have exhausted everything else, before you are allowed to come in. There is no threshold. Patients are seen for pain that sits at a constant four out of ten and interferes with sleep just as appropriately as for pain that is disabling.
What genuinely matters is duration and trajectory. Pain that has persisted beyond six weeks despite reasonable self care, pain that is worsening rather than settling, pain that has started radiating into a limb, or pain that is changing how you live are all reasonable reasons to be evaluated. Certain symptoms should never wait for a threshold at all. Progressive weakness, loss of bowel or bladder control, numbness in the groin, fever alongside back pain, or back pain following significant trauma need urgent assessment.
Want live answers?
Connect with a NY Spine Medicine expert for fast, friendly support.
Myth Six: Steroid Injections Are Dangerous And Strictly Limited
Patients frequently arrive believing that steroid injections destroy bone, that they cause the weight gain oral steroids can, or that you are permitted only three in a lifetime. The picture is more nuanced. Corticosteroids do carry real effects when used repeatedly and at high total exposure, which is exactly why physicians limit frequency and total dose over time.
The commonly cited limit of three injections a year is a rule of thumb rather than a law, and the decision is individualized based on your response, the site treated, your bone density, and whether you have diabetes. Short term effects can include a temporary rise in blood sugar, a few days of flushing or difficulty sleeping, and a brief flare of pain before relief begins. Those are worth knowing about. They are also very different from the blanket warning that keeps people away from treatment that would have helped.
Myth Seven: Pain Management Means Giving Up On Being Active
Some patients avoid a pain practice because they think it means accepting a smaller life, a permanent label, and a list of things they can no longer do. The actual goal is the opposite. Every reasonable plan is built around function, and the questions we ask are about what you want to get back to rather than only about how much it hurts.
Rest is the intervention patients most often choose for themselves, and beyond the first day or two it is usually the wrong one. Prolonged rest weakens the muscles that support your spine, stiffens the joints, and makes the nervous system more protective, which lowers your threshold for pain. Spine care has pointed in the same direction for a long time. Movement, adjusted appropriately, beats rest for most back and neck problems.
That does not mean pushing through anything. It means graded activity, guided by a therapist, with load that increases as tolerance improves. Patients regularly return to running, lifting, tennis, gardening, and picking up their grandchildren after treatment. Some activities get modified, and a few genuinely need to change. But the plan is built to expand what you can do, not to shrink it, and any plan that only tells you what to stop doing is incomplete.
The same applies to work. Total time off is rarely the best answer for spine pain, and modified duty with clear physical restrictions usually produces a better outcome than sitting at home waiting to feel normal. If your restrictions are written vaguely, ask for specifics, because a restriction your employer can actually apply is the one that protects you.
Myth Eight: If The First Procedure Does Not Work, Nothing Else Will
This is the myth that ends treatment prematurely, and it is worth taking apart carefully. A procedure that does not help is not proof that your pain is untreatable. Far more often it means the target was wrong, and that is useful information rather than a dead end. Very little in interventional pain management is a single shot at a single answer.
Spines commonly have more than one pain generator. A patient can have an irritated nerve root and arthritic facet joints at the same time, and treating one can uncover the other. An injection at the wrong level, in a spine where two levels look similar on imaging, produces a poor response for a purely technical reason. Sometimes the source turns out to be the sacroiliac joint or the hip rather than the spine at all. Each of those situations has a different answer, and none of them is nothing.
What should happen after a poor result is a reassessment, not a repetition. Your physician should be asking what the response actually was, whether the immediate anesthetic phase differed from the following weeks, whether the pain has changed location or character, and what the exam shows now. That conversation frequently redirects the workup productively. A good practice keeps a clear record of what has been tried and what it produced, which is what prevents the same loop from repeating. Repeating an identical injection a third time after two clear failures is not a plan, and you are entitled to ask what the reasoning is.
The range of options is also wider than most patients realize. Beyond epidurals and facet blocks there are medial branch blocks and radiofrequency ablation, sacroiliac joint injections, peripheral nerve blocks, kyphoplasty for painful vertebral fractures, regenerative approaches, and spinal cord stimulation for selected patients with severe nerve pain that has not responded to anything else. Add physical therapy, medication management, and treatment of contributing conditions, and the picture looks far less like a single test you either pass or fail.
What To Expect When You Actually Walk In The Door
If there is one thread running through all eight of these myths, it is the assumption that pain management is a single thing: a pill, a shot, a last resort, a verdict. It is a process of narrowing down which structure is causing your symptoms and treating that structure as precisely as the evidence allows, with rehabilitation attached to it.
A first visit is mostly conversation and examination. Where the pain is, what it does, what makes it worse, what you have already tried, and what you want to get back to. Existing imaging is reviewed rather than repeated. You should leave with a working diagnosis in plain language and a plan with a timeline, not simply an appointment for a procedure.
At NY Spine Medicine, our Manhattan and Brooklyn offices combine diagnostic evaluation, image guided interventional treatment, and in house physical therapy, so the plan holds together instead of arriving in pieces from different providers. If you have been putting off an evaluation because of something you heard, call 212-750-1155 and get an answer based on your spine rather than someone else’s story.