Summary:
Almost everyone has a stiff neck sometimes. You sleep at a bad angle, spend a week hunched over a laptop, look down at your phone on the subway for an hour, and it aches. Most of the time it fades and you never think about it again.
So the useful question is not whether neck pain is serious, because usually it is not. The useful question is which features separate the ordinary kind from the kind that deserves an appointment, and which separate that from the small set of situations that deserve an emergency room.
Here is how physicians actually sort that out, so you can apply the same logic to your own neck before you decide to keep waiting.
The Neck Pain Most People Can Safely Wait Out
Mechanical neck pain, sometimes called muscular or postural neck pain, is by far the most common kind. It is achy rather than sharp, it sits in the neck and across the upper shoulders, and it tends to be worse at the end of the day or after a long stretch in one position.
It usually comes with stiffness and reduced rotation. Turning to check a blind spot hurts. Certain positions relieve it. Heat helps, movement helps once you get going, and it improves gradually rather than all at once.
That combination, pain confined to the neck and shoulder region, no symptoms in the arms, no neurologic change, and a trajectory that is clearly improving, describes something you can reasonably manage at home for a couple of weeks with gentle movement, posture adjustments, and simple over the counter measures.

How Long Should Neck Pain Last Before You Worry?
Two to three weeks is a fair benchmark. Ordinary mechanical neck pain generally shows clear improvement inside that window, even if it has not fully resolved. What matters more than the exact number is direction. Pain that is noticeably better than it was last week is following the expected course. Pain that is unchanged, or worse, after three weeks is not.
Plateau is the pattern to watch for. Many people describe an episode that improved quickly for the first ten days and then simply stopped, leaving them at a level they can live with but never fully lose. That plateau often means something structural is involved, a facet joint that has become arthritic and inflamed, a disc that has lost height, or a nerve that is mildly compressed, and it will not resolve just because more time passes.
Recurrence is the other pattern. Neck pain that returns every few months, always in the same place, always triggered by the same activity, is telling you about an underlying mechanical problem rather than a run of bad luck. Each episode may resolve on its own, but the pattern itself is worth investigating.
Severity is a less reliable signal than people expect. A muscle spasm can be genuinely awful for several days and mean nothing at all. A quietly compressed nerve root can produce moderate pain and cause lasting problems. Do not use how much it hurts as your only guide.
Night pain is worth separating out. Neck pain that wakes you consistently and does not ease when you change position is a different pattern from pain that is annoying when you roll over. Combined with fever, unexplained weight loss, or a history of cancer, it is a reason to be evaluated without waiting for the three week mark.
What Symptoms in Your Arms and Your Hands Are Telling You
The moment neck pain stops being confined to the neck, the clinical picture changes. Pain, numbness, tingling, or weakness that travels into the shoulder blade, down the arm, or into specific fingers suggests cervical radiculopathy, a nerve root in the neck being compressed or irritated where it exits the spine.
The distribution is informative. Symptoms into the thumb and index finger, symptoms into the middle finger, and symptoms into the ring and small fingers each correspond to different nerve roots, and a physician can often name the level before ordering imaging. If you can describe exactly which fingers go numb, you are handing your doctor real diagnostic information.
Certain movements provoke it. Tilting the head toward the painful side and looking up often reproduces arm symptoms when a nerve root is compressed. Many patients discover on their own that resting a hand on top of the head relieves the arm pain, which is a classic sign and worth mentioning at your visit.
Weakness matters more than numbness. Trouble lifting your arm overhead, a grip that has weakened enough that you drop things, difficulty with buttons or keys, all suggest the nerve is losing motor function rather than just sending irritated signals. That should be evaluated within days.
Then there is the pattern that is not radiculopathy at all. Clumsiness with fine motor tasks in both hands, changes in your handwriting, a sense that your balance or your gait has become unsteady, or heaviness in the legs alongside neck pain can indicate cervical myelopathy, pressure on the spinal cord itself. This is not a wait and see situation, and it is the reason a physician will ask about your walking when you came in about your neck.
Want live answers?
Connect with a NY Spine Medicine expert for fast, friendly support.
Neck Pain That Needs Emergency Care, Not an Appointment
Neck pain following significant trauma, a car accident, a fall down stairs, a sports collision, needs imaging before anyone manipulates or stretches anything. That is especially true if you are older or have osteoporosis, where a fracture can happen with far less force than you would expect.
Neck pain with fever, particularly with severe stiffness that makes it hard to bring your chin toward your chest, or following a recent infection, needs same day evaluation. Spinal infections and meningitis are uncommon, but they are time sensitive.
Sudden severe weakness in the arms or legs, loss of bowel or bladder control, or a rapid change in coordination alongside neck pain should send you to an emergency department. So should a severe headache at the base of the skull that came on abruptly and feels unlike anything you have had before.
What a Thorough Neck Pain Evaluation Should Actually Involve
A real evaluation starts with a conversation that goes well beyond where it hurts. When did it start, what were you doing, what makes it better and worse, has it changed over time, and critically, has anything changed about your hands, your balance, or your walking. Those last questions are the ones that separate an ordinary neck from one that needs urgency.
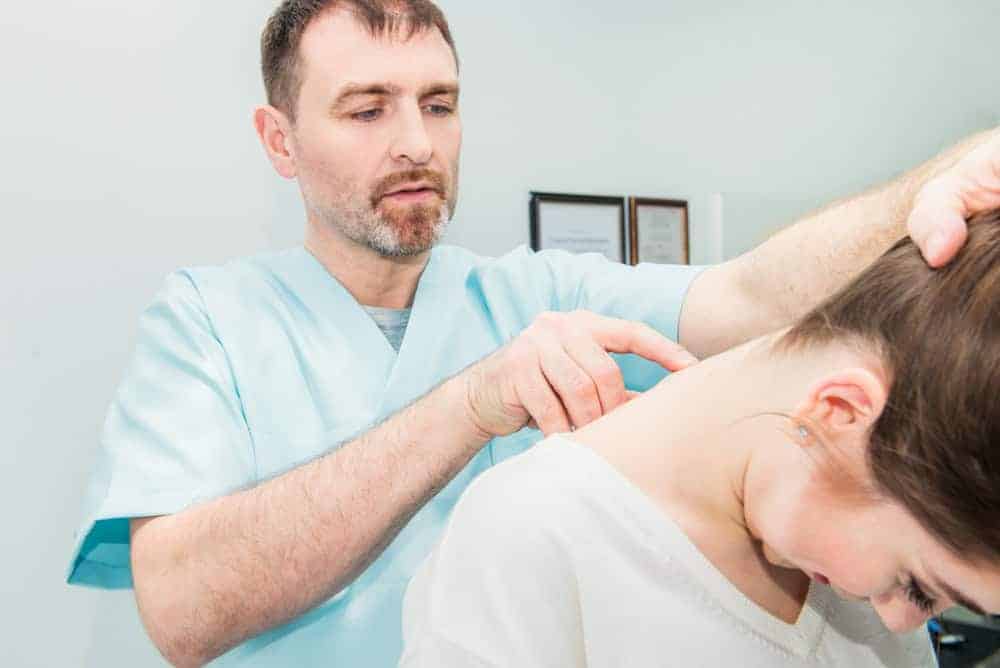
The physical exam checks range of motion in every direction, palpates the muscles and the facet joints along the back of the neck, and tests reflexes, strength, and sensation in both arms. Provocative maneuvers are used to see whether a nerve root reproduces your symptoms. Gait and coordination are assessed whenever there is any suspicion of spinal cord involvement.
Imaging is chosen for a reason rather than reflexively. X-rays show alignment, disc height, and arthritic change, and they are useful after trauma or when instability is a question. An MRI shows the discs, the nerve roots, and the spinal cord, which is what you need when arm symptoms or myelopathic signs are present.
Electrodiagnostic testing has a specific role. EMG and nerve conduction studies distinguish a compressed nerve root in the neck from a peripheral nerve problem such as carpal tunnel syndrome, which can produce overlapping hand symptoms. Patients are sometimes treated for months for the wrong one of those two.
The output of all this should be a named problem, not a shrug. Facet mediated neck pain, cervical radiculopathy at a specific level, myofascial pain, cervicogenic headache, or degenerative change in a particular pattern. A specific answer is what makes a specific treatment plan possible.
Treatment Options for Neck Pain That Has Not Resolved on Its Own
Physical therapy remains the foundation for most persistent neck pain, and the version that works is more than heat and a massage. It typically involves restoring motion at stiff segments, strengthening the deep stabilizing muscles of the neck, addressing the shoulder blade mechanics that load the cervical spine, and correcting the workstation and phone habits that keep reproducing the problem.
Medial branch blocks and facet joint injections are used when the small paired joints along the back of the neck are the suspected source, which is common in patients whose pain is worse with extension and rotation. These injections are diagnostic first. If a block reliably takes the pain away for the duration of the anesthetic, that joint is confirmed as the source.
Cervical radiofrequency ablation follows for patients whose blocks confirm facet mediated pain. Heat is applied to the tiny medial branch nerves that carry pain signals from those joints, interrupting them. Relief commonly lasts many months, and because the nerves eventually regenerate, the procedure can be repeated when symptoms return.
Cervical epidural steroid injections are used when a nerve root is inflamed, typically from a disc herniation or narrowing where the nerve exits. Delivered under fluoroscopic guidance, the steroid reduces inflammation around the root. For many patients with radiculopathy, that is what makes the difference between managing the problem and simply enduring it.
Trigger point injections, regenerative approaches, and careful medication management fill in around the edges depending on the diagnosis. Surgery is reserved for a small group, most clearly for cervical myelopathy, where decompression is aimed at protecting the spinal cord rather than only relieving pain, and for radiculopathy with progressive weakness that has not responded to anything else.
What ties all of this together is sequence. Injections that are not connected to a rehabilitation plan tend to buy temporary relief. Rehabilitation attempted through pain that is too severe tends to fail. Getting the order right is most of the skill.
Deciding Whether It Is Time to Have Your Neck Looked At
The practical rule is simpler than it looks. If your neck pain is confined to your neck, improving week over week, and not affecting your arms, hands, balance, or walking, waiting is reasonable. If it has plateaued past a few weeks, keeps returning, or has produced any symptom below the shoulder, it has earned a professional look. And if there is weakness, fever with stiffness, recent trauma, or any change in coordination or bladder control, it should not wait at all.
At NY Spine Medicine, our Manhattan and Brooklyn physicians evaluate neck pain with exactly that hierarchy in mind. We have EMG and nerve conduction testing available in office to sort out arm and hand symptoms, we perform image-guided cervical injections and radiofrequency procedures when the diagnosis supports them, and we keep physical therapy under the same roof so the plan is one plan rather than three. We also handle workers compensation and auto injury claims, including the whiplash cases that so often start as a neck that seemed fine at the scene.
If you are not sure whether your neck pain needs attention, call us at 212-750-1155 and we will help you make that call properly.